

 May 20, 2025
 4 min read
Kidney Stones: Passing One, and Preventing the Next

Kidney stones are common, and more common in hot countries, where people lose more water through sweat and pass less, more concentrated urine. In Pakistan and the Middle East, rates are among the highest in the world. Once you've had one stone, the chance of another is high, roughly one in two within ten years without prevention. Most of that risk can be reduced with a few habits, some of which go against common advice.
How stones form
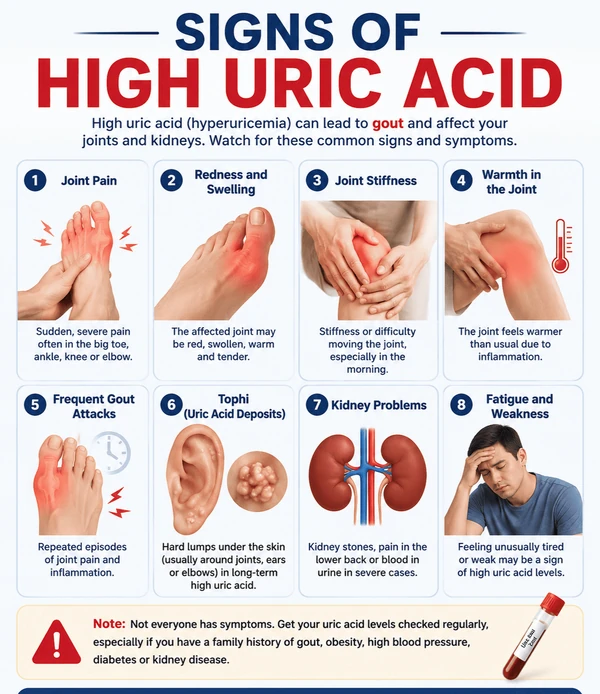
Urine contains dissolved minerals such as calcium, oxalate, uric acid and phosphate. When there is too much mineral and too little water, crystals form and grow into stones. About 80% of stones are calcium-based, mostly calcium oxalate. Others are made of uric acid (linked to gout, obesity and diabetes), struvite (from certain urine infections) or, rarely, cystine (an inherited condition). Knowing the type, from a stone that is caught and analysed, helps target prevention.
Symptoms
Stones sitting in the kidney often cause no symptoms. When one moves into the ureter, the narrow tube to the bladder, it causes renal colic: sudden, severe pain in the side or back, often spreading to the groin, coming in waves. People with renal colic can't keep still, unlike most other causes of severe abdominal pain. Nausea, vomiting, blood in the urine and an urgent need to pass urine are common.
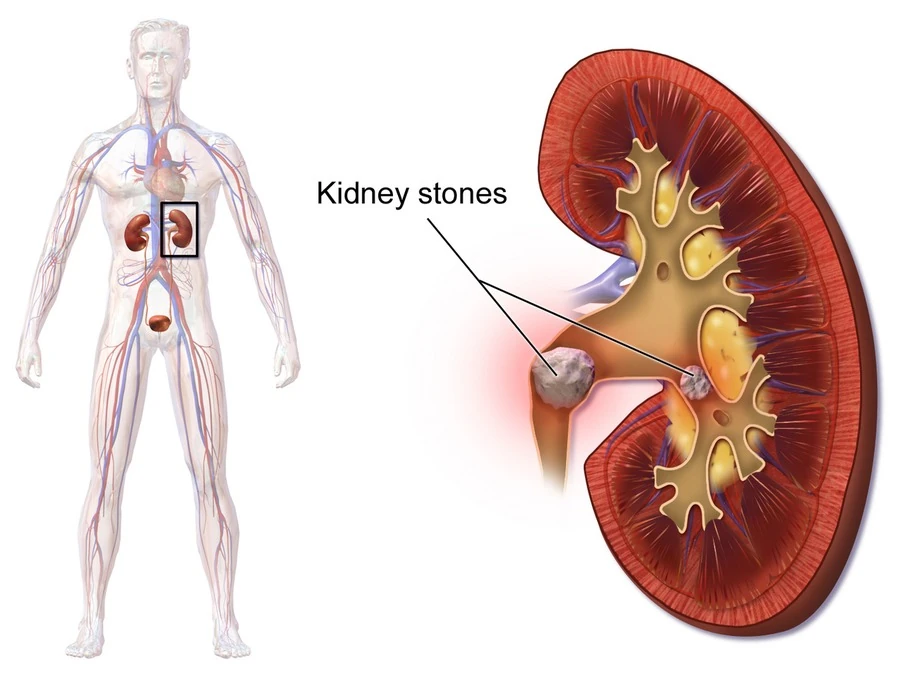
Most stones under 5 mm pass by themselves within a few weeks. Image: Blausen Medical / Wikimedia Commons, CC BY 3.0
Passing a stone
Most stones under 5 mm pass by themselves within a few weeks. Larger stones are less likely to pass.
- Pain relief. Anti-inflammatory painkillers (diclofenac, ibuprofen) are the first choice for renal colic. They work at least as well as opioids, with fewer side effects, if they are safe for you (no kidney disease, ulcers or relevant heart problems).
- Tamsulosin, a medicine that relaxes the ureter, can help stones of 5 to 10 mm near the bladder pass.
- Procedures for stones that won't pass: shock-wave lithotripsy (breaking the stone from outside), ureteroscopy (a thin telescope through the bladder) or, for large kidney stones, keyhole surgery through the back.
Emergency warning: a stone with fever or shivering can mean an infected, blocked kidney. This can lead to sepsis within hours and needs hospital treatment the same day. The same applies to anyone with a single kidney, or who passes little or no urine.

Drinking enough to pass about 2.5 litres of urine a day is the single most effective step. Photo: Tima Miroshnichenko / Pexels
Preventing the next one
1. Drink enough to pass about 2.5 litres of urine a day. This is the single most effective step. In practice it often means drinking 2.5 to 3 litres a day, more in hot weather or with heavy work. Spread it through the day and include a glass before bed. Urine should look pale. Water is best. Adding lemon juice provides citrate, which helps stop crystals forming.
2. Don't cut out calcium. This is the most common mistake. Calcium from food binds oxalate in the gut, so it is never absorbed. Cutting dairy lets more oxalate through to the urine. In a five-year Italian trial, men with recurrent calcium stones were given either a low-calcium diet or a diet with normal calcium, low salt and less animal protein. The normal-calcium diet cut recurrence by about half. Aim for normal calcium intake from food, with meals.
3. Cut down on salt. Extra sodium makes the kidneys pass more calcium into urine. Processed foods, pickles, salty snacks and restaurant meals are the main sources.
4. Moderate meat. Large amounts of meat, chicken and fish raise uric acid and calcium in the urine and lower citrate.
5. Be sensible with high-oxalate foods. For people who make calcium oxalate stones, large amounts of spinach, rhubarb, beetroot, nuts, strong black tea and chocolate add oxalate. Eating them with a calcium-containing food reduces the effect. You don't have to avoid them entirely.
6. Limit sugary drinks, especially those sweetened with fructose, which are linked with a higher stone risk.
Medicines and supplements
Some medicines raise stone risk. These include the epilepsy and migraine drug topiramate, acetazolamide, high-dose vitamin C supplements (1 g a day or more, which the body converts partly into oxalate), and calcium supplements taken between meals rather than with them. Discuss changes with your doctor rather than stopping anything yourself.
For people who keep forming stones despite these steps, a 24-hour urine collection shows exactly what is driving them. Medicines can then help. Potassium citrate raises urine citrate and can dissolve uric acid stones. Thiazide diuretics lower urine calcium. Allopurinol lowers uric acid.
The UK guideline on renal and ureteric stones (NICE NG118) and the NHS kidney stones page give more detail.
Sources
- Borghi L, Schianchi T, Meschi T, Guerra A et al., "Comparison of Two Diets for the Prevention of Recurrent Stones in Idiopathic Hypercalciuria", New England Journal of Medicine 346 (2002): 77-84. https://doi.org/10.1056/NEJMoa010369
- NICE, "Overview - Renal and ureteric stones: assessment and management - Guidance". https://www.nice.org.uk/guidance/ng118
- NHS, "Kidney stones". https://www.nhs.uk/conditions/kidney-stones/




Comments (0)
Leave a Reply
Comments are moderated. Please read our Comment Policy before posting.
Log in to post a comment.