

 Mar 21, 2025
 4 min read
Diabetic Foot Problems: Daily Checks That Prevent Ulcers and Amputation
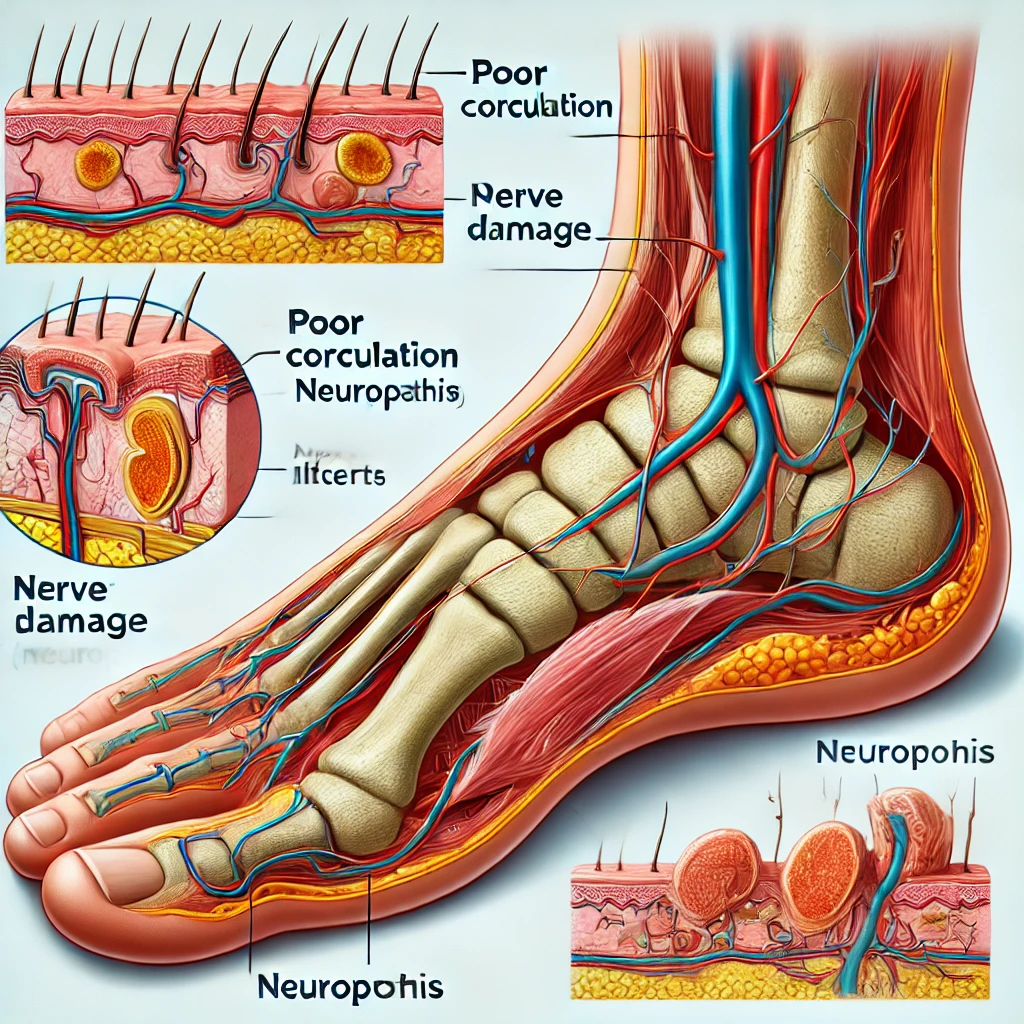
Between a fifth and a third of people with diabetes will develop a foot ulcer at some point in their lives. Once an ulcer has healed, about 40% come back within a year (NEJM review, 2017). Most diabetes-related amputations begin with an ulcer that started small: a blister from new shoes, a burn from a hot floor, or a crack in dry skin that went unnoticed. A few minutes of attention to the feet each day prevents most of them.
Why diabetes puts feet at risk
Nerve damage (neuropathy). Years of high blood sugar damage the long nerves to the feet first. The feet lose the ability to feel pain, heat and pressure, so a stone in a shoe or a burn goes unnoticed. Damage to the nerves that control sweating leaves skin dry and cracked. Damage to the nerves that control the small foot muscles changes the foot's shape, creating pressure points.
Poor circulation (peripheral arterial disease). Narrowed arteries in the legs mean less blood reaches the feet, so wounds heal slowly or not at all. Smoking makes this much worse.
Infection. High blood sugar weakens the body's defences, so an infected ulcer can spread to deeper tissue and bone quickly, sometimes without much pain or fever.

Look at your feet every day, including the soles, using a mirror if needed. Photo: Natalia Lara / Pexels
Daily foot care
- Look at your feet every day, including the soles and between the toes. Use a mirror or ask someone to help. Look for cuts, blisters, red areas, swelling, hard skin and changes in colour.
- Never walk barefoot, indoors or out. Hot ground, beach sand and tiled floors at places of worship or washing areas cause serious burns in people who can't feel heat.
- Test bath water with your elbow or a thermometer, not your feet. Don't put feet near heaters or use hot-water bottles on them.
- Wash daily and dry carefully, especially between the toes. Moisturise the tops and soles, but not between the toes, where moisture encourages fungal infection.
- Cut toenails straight across and file sharp edges. If you can't see or reach well, or your nails are thick, have a podiatrist do it.
- Don't use corn plasters or "corn removers". They contain salicylic acid, which can burn through skin that can't feel, creating an ulcer. Have corns and hard skin treated by a podiatrist.

Badly fitting shoes are the most common cause of foot ulcers. Photo: iram shehzad / Pexels
Shoes
Badly fitting shoes are the most common cause of ulcers. Choose shoes with enough room for the toes, soft uppers and fastenings (laces or straps) that stop the foot sliding forward. Buy them in the afternoon, when feet are slightly swollen. Break new shoes in gradually, an hour or two at a time, and check your feet afterwards. Shake out and feel inside shoes before putting them on. Wear socks without tight tops or thick seams. Thin sandals and backless slippers give little protection.
Check-ups
Everyone with diabetes should have their feet examined at least once a year. The check includes a nylon monofilament test for feeling, checks of foot pulses, and a look at skin and foot shape. The result places you in a risk category that decides how often you need specialist foot care. The international diabetic foot guidelines (IWGDF) set out the standards.
Better blood sugar control slows nerve damage. Controlling blood pressure and cholesterol, and stopping smoking, protect circulation.
Conditions to recognise early
Foot ulcers are most common on the ball of the foot, the tips of the toes and over bunions. Any break in the skin that hasn't started healing within a few days needs professional care. Taking pressure off the ulcer is essential for healing. This often means a special boot or cast.
Charcot foot is a less well-known emergency. In someone with neuropathy, bones and joints in the foot weaken and start to fracture and collapse. The foot becomes hot, red and swollen, often with little pain. It is commonly mistaken for a sprain, gout or cellulitis. Without early immobilisation, the foot can become permanently deformed and develop ulcers. A hot, swollen foot in someone with diabetes and neuropathy needs same-day assessment.
Fungal infections of the skin and nails are common. Cracks from athlete's foot let bacteria in, so treat them promptly.
Get help the same day if you notice
- a new wound, blister or break in the skin that isn't healing
- redness, warmth, swelling or a bad smell from the foot
- pus or discharge on your sock
- a foot that is suddenly hot and swollen
- a toe that turns black or blue
- fever or feeling unwell with a foot problem
Fast treatment in the first days of a foot problem is what most often saves limbs.
Sources
- Armstrong D, Boulton A, Bus S, "Diabetic Foot Ulcers and Their Recurrence", New England Journal of Medicine 376 (2017): 2367-2375. https://doi.org/10.1056/NEJMra1615439
- iwgdfguidelines.org, "IWGDF Guidelines - International Working Group on the Diabetic Foot". https://iwgdfguidelines.org/
- NICE, "Overview - Diabetic foot problems: prevention and management - Guidance". https://www.nice.org.uk/guidance/ng19




Comments (0)
Leave a Reply
Comments are moderated. Please read our Comment Policy before posting.
Log in to post a comment.